

Maternal and child health (MCH) remains a cornerstone of global public health and a pivotal driver of progress towards the Sustainable Development Goals (SDGs), particularly SDG 3.2, which calls for reducing neonatal mortality rate (NMR) to at least as low as 12 per 1000 live births and under-five mortality rate (U5MR) to 25 per 1000 by 2030 [1,2]. The NMR can serve as a sensitive sentinel indicator, reflecting the real-world effectiveness and resilience of MCH systems. Despite concerted global efforts, the SDG 3.2 target for neonatal survival remains unattainable for many countries. In 2023, an estimated 2 million neonatal deaths occurred globally, with over 70% concentrated in low- and middle-income countries (LMICs), where fragile health systems, inequitable access, and persistent poverty coverage to undermine perinatal survival [3]. The burden is especially acute in settings where multiple systemic challenges intersect. In Nigeria and India, accounting for nearly one-third of global neonatal deaths, high rates of unattended births coincide with unreliable essential medicine supply chains drastically limit access to life-saving care [4,5]. Elsewhere, critical human resource shortages (e.g. Malawi, Tanzania) [6,7], recurrent stockouts of essential drugs (e.g. Pakistan, Haiti) [8], and the collapse of basic infrastructure in conflict zones (e.g. South Sudan, Central African Republic) [9,10] converge to cripple perinatal services and compromise maternal and newborn survival.
Over the past three decades, China has achieved unprecedented global reductions in NMR, reducing it from exceeding 30 per 1000 live births in the early 1990s to below 3 per 1000 in 2023, and surpassing the SDG 3.2 target more than seven years ahead of schedule [2]. This achievement is even more remarkable given China’s vast geographic heterogeneity, significant urban–rural divides, and initial disparities in healthcare infrastructure. However, this extraordinary trajectory is not accidental but driven by systematic, nationwide health system reforms initiated in the 1990s. Key initiatives, notably the Reducing Maternal Mortality and Eliminating Neonatal Tetanus (RME) project and the New Rural Cooperative Medical Scheme (NRCMS), dramatically expanded financial risk protection and institutional delivery coverage in rural areas, facilitating rapid scale-up of critical MCH services such as hospital delivery, systematic maternal health management, postpartum visit, and early newborn care [11,12]. Implemented from 2000 to 2010, the RME project targeted poor rural counties through the establishment of obstetric emergency networks, training of village-level birth attendants, and subsidisation of hospital deliveries. It was later integrated into China’s national basic public health service package. The NRCMS, piloted in 2003 and achieving near-universal rural coverage by 2008, provided government-subsidised inpatient insurance that dramatically reduced financial barriers to facility-based childbirth before being merged into the Urban–Rural Resident Basic Medical Insurance in 2016.
Despite growing documentation of improvements in MCH outcomes in China, most existing studies rely on conventional time series or single-indicator approaches that fail to capture localised trends, inflection points, and dynamic interdependences among key indicators such as maternal mortality ratio (MMR), U5MR, infant mortality rate (IMR), and NMR [13,14]. While descriptive analyses highlight overall progress, they obscure the complex, nonlinear pathways through which sustained reductions have been achieved. Methodologically, standard models, such as ordinary least squares and fixed effects models, often overlook the cumulative impacts of phased policy implementation and the feedback mechanisms among mortality indicators. In contrast, the Joinpoint regression model enable identification of both global trends and critical turning points in temporal trajectories [15], while vector error correction model (VECM), known as an extension of vector autoregressive model, can disentangle short-term fluctuations from long-term equilibrium adjustments by modelling cointegrated non-stationary time series [16].
To address these gaps, this study leverages China’s nationally representative longitudinal data (1991–2023), within a VECM framework to dissect the dynamic equilibria among MMR, U5MR, IMR, and NMR to quantify the specific contributions of key national policies (e.g. NRCMS, RME project) alongside critical health service coverage metrics (e.g. hospital delivery, maternal system management, postnatal visit, and newborn visit) to the temporal trajectories of these mortality indicators. These findings provide critical leverage to accelerate progress towards SDG 3.2 in resource-limited and fragmented health systems, informing the design of responsive and equity-focused policies that simultaneously reduce neonatal mortality and strengthen long-term health system resilience.
METHODS
Definitions
The MMR refers to the number of maternal deaths per 100 000 live births in a given year. The NMR, IMR, and U5MR are defined as the number of deaths occurring before 28 days, 1 year, and 5 years of age, respectively, per 1000 live births in a given year.
Data source and processing
Data on national MMR, U5MR, IMR, and NMR from 1991 to 2023 were obtained from the National Bureau of Statistics of China. The maternity and child health data within this national dataset were collected through China’s National Maternal and Child Mortality Surveillance System, which employed stratified cluster random sampling to select monitoring units, along with stringent reporting and quality control measures to ensure data accuracy and integrity. The final dataset encompassed 31 provinces and municipalities across China. The data used in this study including hospital delivery rate, maternal systematic management rate, postpartum visit rate, and neonatal visit rate were collected from the National Report on Maternal and Child Health Information Analysis. The data above along with their definitions are presented (Tables S1–3 in the Online Supplementary Document).
Owing to the dimensional differences among MMR, U5MR, IMR and NMR, MMR was converted from per 100 000 to per 1000 live births, aligning with U5MR, IMR, and NMR. All indicators subsequently underwent Z-score standardisation to facilitate subsequent modelling and statistical analysis. Standardisation was performed using:

where X is the raw value, μ is the variable mean, and σ is the standard deviation. This generated mean-centred, unit-variance distributions for comparative analysis and multivariate modelling.
Meantime, exogenous variables, including the hospital delivery rate, maternal systematic management rate, postpartum visit rate, and neonatal visit rate were incorporated into the model. Missing values for these indicators were addressed using time-series interpolation (e.g. spline interpolation) followed by Z-score standardisation. In addition, to capture the phased implementation and progressive impact of key health policies, this study operationalised the NRCMS and RME project as non-binary policy variables [17,18]. Reflecting the gradual strengthening of policy effects, NRCMS was coded as:
0 prior to 2003 (non-implementation)
0.5 during the 2003–2008 pilot phase
0.75 from 2008–2016 (full-coverage promotion)
1 post-2016 (following its integration into the urban-rural resident medical insurance system).
Similarly, the RME project was assigned:
0 pre-2000 (non-implementation)
0.5 from 2000–2010 (pilot and national rollout)
1 after 2010 (incorporation into China’s national basic public health service).
This step-function coding design quantitatively mirrors each policy’s maturity trajectory.
This study utilised exclusively aggregated, publicly available national statistics with no personal identifiers; therefore, no ethics approval or informed consent is needed.
Average annual percent change
Joinpoint regression analysis [15] was adopted to analyse the temporal trends of MMR, U5MR, IMR, and NMR at the national level. It can identify the points with remarkable changes in trend, divide the overall trend into multiple subsegments based on these observed joinpoints, and further assess the epidemiological trend of each subsegment by calculating the annual percentage change (APC):

Moreover, the average annual percent change (AAPC), which serves as a summary measure of the trend over a prespecified fixed interval, is also calculated as a weighted average of APC by the span width of segmented interval. Its computation formula is:

where ωi for each interval of the year, and βi is the regression coefficient for each interval. If the APC or AAPC>0, an increasing trend is recognised within one certain period. In contrast, if the APC or AAPC estimation <0, a decreasing trend is recognised within one certain period. Otherwise, the trend is recognised to be stable.
Pearson correlation analysis
Pearson correlation [19,20], a type of statistical tool used to measure the linear relationship between two variables that are continuous, was used in this study. And its coefficient, ranging from −1 to +1, indicates both the direction and the strength or weakness of the relationship.
Vector error correction model
The VECM is an extension of the vector autoregressive model that incorporates the concept of cointegration to mitigate the spurious regression problem that may arise when dealing with non-stationary time series [16]. The VECM includes the first differences of the variables replacing initial non-stationary data, lagged differences of the variables, and an error-correction term (ECT). Central to this framework, the ECT quantifies how variables adjust toward long-term equilibrium following short-term deviations and acts as a corrective mechanism driving variables back towards their cointegrating relationship. The values of ECT are derived from cointegrating vectors identified through the Johansen test. In VECM, several procedures must be passed including unit root test, cointegration test, Granger causality test, and impulse response function analysis.
Unit root test
The unit root test is a critical preliminary step in VECM modelling to verify the stationarity of the variables. If the original time series data are non-stationary, sequential first- or second-order differencing is applied. Should the differenced series remain non-stationary at conventional significance levels (e.g. 5%), acceptance of stationarity at the 10% significance level may be considered to avoid excessive differences leading to excessive information loss, inaccurate estimation of model parameters and degraded predictive performance inherent in higher-order integration. Furthermore, a core condition for employing the VECM framework is that the model variables are integrated of the same order, typically first-order stationary (I (1)). The augmented Dickey-Fuller (ADF) test was used to determine the stationarity of variables and their order of integration in this study.
Cointegration test
Johansen’s cointegration test is also an essential prerequisite that the VECM model can be used. This procedure generates two statistical measures, namely trace statistic and maximum eigenvalue. The Johansen’s cointegration test is sequential testing starting with the null hypothesis τ0: τ = 0 (no cointegration) against τ1: τ≥1. Failure to reject τ0 indicates no cointegrating relationships. Rejection implies at least one cointegrating vector, prompting subsequent tests of τ0: τ≤1 until non-rejection occurs.
Granger causality test
Granger causality examines the ability of past values of one time series variable to offer information or predict future values of another variable. The significance level of the Granger causality test is set as 5%. When the P-value of the Granger causality test is less than the significance level, it is proved that the explanatory variable is the Granger cause of the explained variable.
Diagnostic test
To guarantee the fitness of the constructed model, this study investigates the robustness of the VECM by investigating the serial correlation and normality tests to make unbiased statistical inferences.
Statistical analysis
All analyses were performed using R statistical software, version 4.4.3 (R Foundation for Statistical Computing, Vienna, Austria), with the exception of Joinpoint regression, which was conducted using the Joinpoint Regression Program, version 5.4.0.0 (Surveillance Research Program, National Cancer Institute, Bethesda, Maryland, USA). A P-value less than 0.05 was considered statistically significant.
RESULTS
Temporal trends of MMR, U5MR, IMR, and NMR
The national MMR, U5MR, IMR, and NMR in China showed overall downward trends from 1991 to 2023 (Figure 1). The national MMR, U5MR, IMR, and NMR decreased from 80 per 100 000 live births, 61.0‰, 50.2‰ and 33.1‰ in 1991 to 15.1 per 100 000 live births, 6.2‰, 4.5‰ and 2.8‰ in 2023, respectively. The variation in national MMR showed three phases, and its AAPC was −4.92%. The variation in national U5MR showed three phases, and its AAPC was −6.79%. The national IMR showed six phases, and its AAPC was −7.19%. The national NMR exhibited five distinct phases, and its AAPC was −7.40%.
Figure 1. Trends in MCH outcomes in relation to national policy milestones: a joinpoint regression analysis. *P < 0.05. APC – annual percentage change, MCH – maternal and child health.

Correlations among MMR, U5MR, IMR and NMR
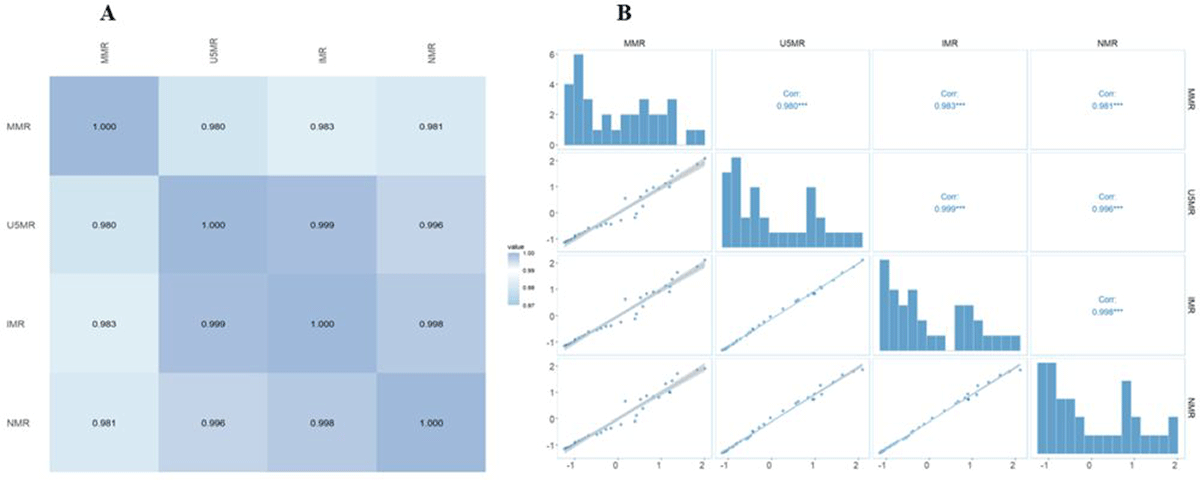
A correlation heatmap quantifies the associations among national MMR, U5MR, IMR and NMR (Figure 2, Panel A). The analysis revealed robust positive correlations across all mortality indicators, with high correlation coefficients (ρ≥0.980). The scatter plot matrix with regression lines further confirmed the positive correlation among mortality indicators while visually illustrating both the direction and strength of the correlation (Figure 2, Panel B).
Figure 2. Heatmap and scatter plot matrix illustrating the correlation coefficients among MMR, U5MR, IMR and NMR. Panel A. Heatmap. Panel B. Scatter plot matrix. IMR – infant mortality rate, MMR – maternal mortality ratio, NMR – neonatal mortality rate, U5MR – under-five mortality rate.
The augmented Dicker-Fuller unit root test
As seen from the comparison of ADF unit root test results at 5% and 10% significance levels (Table 1), the original time series of all variables were almost unstable, except for newborn visit rate and postpartum visit rate. Following the first-order difference, four variables including MMR, IMR, NMR, and hospital delivery rate passed the ADF test, showing stationarity at the 5% significance level. At the 10% significance level, all differenced variables satisfied the stationarity condition. Although some variables failed the stricter 5% significance criterion, the collective evidence of stationarity of first-differenced data supported the validity of the VECM specification.
Table 1. Comparison of ADF unit root test results at 5% and 10% significant level
ADF − augmented Dickey-Fuller test, IMR – infant mortality rate, MMR – maternal mortality ratio, NMR – neonatal mortality rate, U5MR – under-five mortality rate
Johansen cointegration test
On the basis of the Johansen approach to the cointegrated test, the rank test values for both the trace and maximum eigenvalue tests were utilised to examine potential cointegration relationships among all variables. Both the trace and maximum eigenvalue tests indicated the existence of three cointegration relationships at the 5% significance level (Table 2).
Table 2. Johansen cointegration test results
*Statistic >5% critical value. ‘√’ indicates the existence of a cointegration relationship, whereas ‘ × ’ indicates the absence of a cointegration relationship.
Results of VECM estimation
The short-term adjustment parameters revealed distinct equilibrium correction patterns across mortality indicators (Table 3; Tables S4 and S5 in the Online Supplementary Document). For MMR, the model identified significant short-term equilibrium correction through ECT2 (α = −1.34, P = 0.016), indicating 134% overshooting adjustment per period. Concurrently, hospital delivery rate substantially reduced MMR (α = −0.11, P = 0.002), while NRCMS exhibited a counterintuitive positive association (α = 0.50, P = 0.005). The system demonstrated strong self-regulation, with a lagged MMR significantly lowering current mortality (MMR.dl1: α = −0.64, P = 0.009).
Table 3. Significant short-term adjustment parameter (α) results of the VECM estimation
ECT – error-correction term, IMR – infant mortality rate, MMR – maternal mortality ratio, NMR – neonatal mortality rate, NRCMS – Project and the New Rural Cooperative Medical Scheme, RME – Reducing Maternal Mortality and Eliminating Neonatal Tetanus, U5MR – under-five mortality rate
The U5MR demonstrated exceptionally rapid equilibrium restoration, with ECT2 driving a significant 117% overshooting correction per period (α = −1.17, P < 0.001). This adjustment operated concurrently with strong autoregressive control (U5MR.dl1: α = −1.25, P = 0.010). Counterintuitively, maternal system management coverage was associated with short-term U5MR increases (α = 0.51, P = 0.043).
The IMR exhibited dual-pathway equilibrium restoration, with ECT2 driving significant negative adjustment (α = −0.97, P < 0.001) – correcting 97% of disequilibrium per period – while ECT3 provided counter-directional correction (α = 0.77, P = 0.011) at 77% intensity, collectively enabling asymmetric adjustment to mortality shocks across deficit and surplus states. Short-term adjustments revealed that increased newborn visit rates predict lower IMR, with each unit rise associated with a 0.04-unit decline in infant mortality (α = –0.04, P = 0.036). Conversely, the RME project demonstrated a stronger protective effect, reducing IMR by 0.25 units per unit increase in coverage (α = −0.25, P = 0.014). These results suggested that while both interventions reduce infant mortality, the RME project delivered a substantially larger marginal effect.
The VECM estimates revealed rapid short-term adjustment through ECT1, with NMR converging to long-run equilibrium at a rate of 89% per period (α = −0.89, P = 0.030). Counterintuitively, hospital delivery rate exhibited a detrimental short-term association, with each unit increase increasing NMR by 0.05 units (α = 0.05, P = 0.013). Conversely, NRCMS demonstrated a substantial protective effect, reducing NMR by 0.26 units per unit expansion (α = −0.26, P = 0.006). All equations demonstrated robust fit (adjusted R2 = 0.761 ~ 0.909, P < 0.001).
For each mortality indicator, several significant error correction terms (P < 0.05) were extracted to compare their short-term adjustment speeds, including corresponding coefficient estimates and 95% confidence interval (CI) (Figure S1 in the Online Supplementary Document).
The normalised cointegration vectors revealed three long-run equilibrium relationships among maternal and child mortality variables (Table S6 in the Online Supplementary Document). In the first vector (ECT1), NMR was the normalisation variable (β = 1.00) and was negatively cointegrated with MMR (β = −0.65). The second vector (ECT2) showed IMR as the dominant variable (β = 1.00), exhibiting a negative association with MMR (β = −0.74). The third vector (ECT3) featured U5MR as the key component (β = 1.00), also inversely related to MMR (β = −0.89). All vectors included negative constants (ranging from −0.79 to −0.58), confirming stable convergence towards equilibrium.
Granger causality test
Through the Granger causality test, it could be found unidirectional causality relationships that NMR was the Granger cause of MMR, U5MR, and IMR (P < 0.05) (Table S7 in the Online Supplementary Document).
Impulse response function
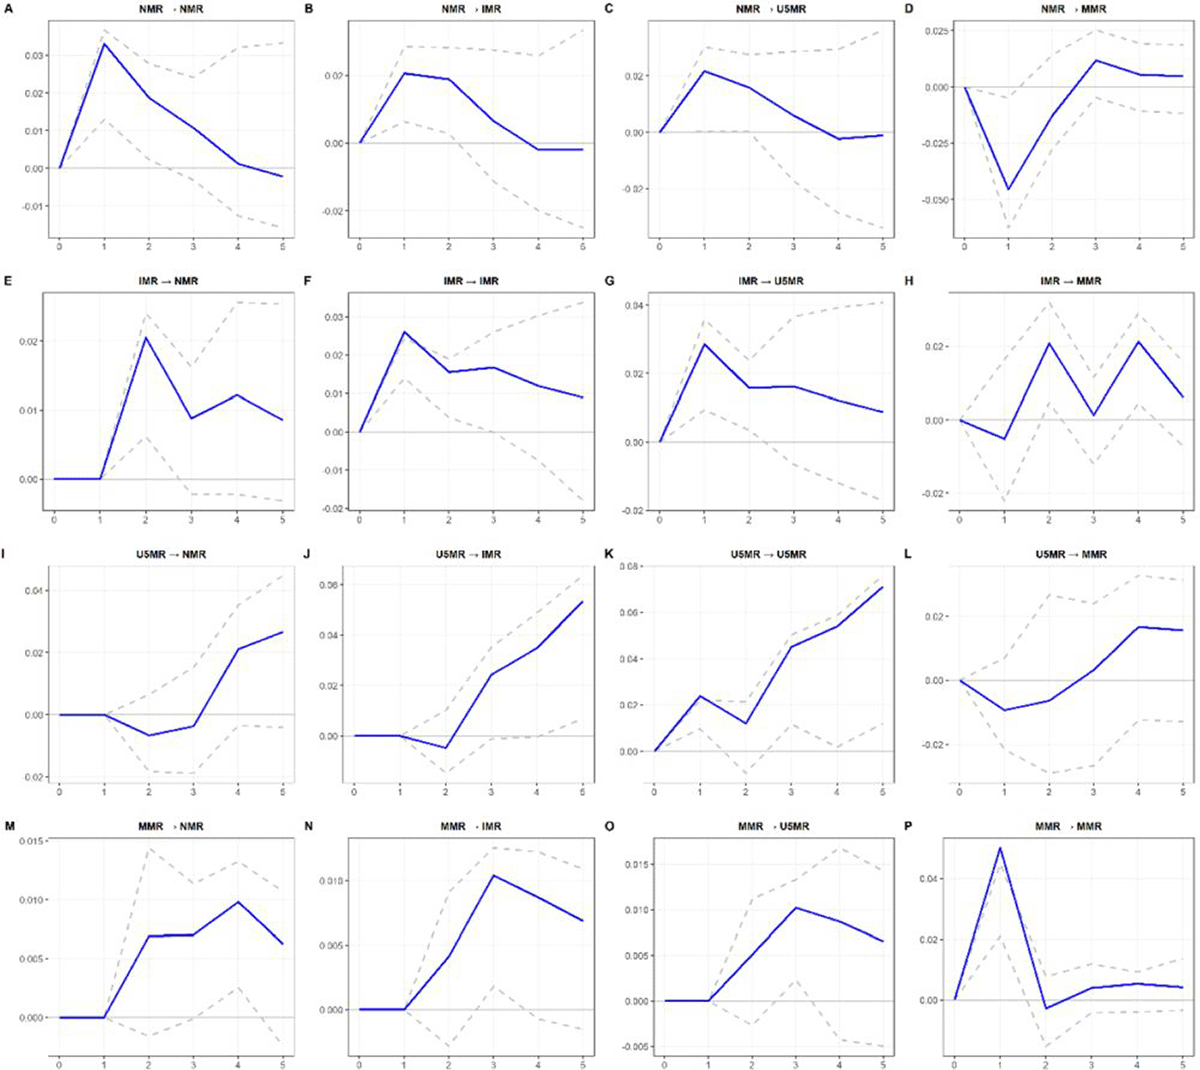
The impulse response diagram depicted the dynamic effect of a variable’s shock on itself or on other variables. The self-shock impacts were consistently positive and NMR, IMR, and MMR reached their peak impacts in the first period before declining (Figure 3, Panel A, Panel F, and Panel P), whereas U5MR followed a different pattern (Figure 3, Panel K). Similarly, the impacts of NMR on IMR and U5MR were consistently positive (Figure 3, Panel B and Panel C), peaking in the first period and subsequently decreasing, whereas the influence of NMR on MMR showed negative shocks during 0–2 periods, shifting to positive shocks thereafter (Figure 3, Panel D). The IMR exhibited persistently positive effects on NMR and U5MR without significant fluctuations from time 1–5, indicating sustained long-term impacts (Figure 3, Panel E and Panel G), whereas the influence of IMR on MMR followed a different pattern (Figure 3, Panel H). The effects of U5MR on NMR and IMR (Figure 3, Panel I and Panel J), along with MMR’s effects on NMR, IMR, and U5MR (Figure 3, Panel M, Panel N and Panel O) exhibited upward growth. In contrast, the impact of U5MR on MMR remained stable growth before peaking in the fourth period (Figure 3, Panel L).
Figure 3. Impulse response diagram. Panel A. Response of NMR to NMR shock. Panel B. Response of IMR to NMR shock. Panel C. Response of U5MR to NMR shock. Panel D. Response of MMR to NMR shock. Panel E. Response of NMR to IMR shock. Panel F. Response of IMR to IMR shock. Panel G. Response of U5MR to IMR shock. Panel H. Response of MMR to IMR shock. Panel I. Response of NMR to U5MR shock. Panel J. Response of IMR to U5MR shock. Panel K. Response of U5MR to U5MR shock. Panel L. Response of MMR to U5MR shock. Panel M. Response of NMR to MMR shock. Panel N. Response of IMR to MMR shock. Panel O. Response of U5MR to MMR shock. Panel P. Response of MMR to MMR shock. IMR – infant mortality rate, MMR – maternal mortality ratio, NMR – neonatal mortality rate, U5MR – under-five mortality rate.
Diagnostic test of VECM
This study assessed the reliability of the VECM estimated coefficients utilising the Portmanteau and Jarque-Bera test collectively, indicating that residuals were normally distributed and free from serial correlation (Portmanteau test P-value = 0.37; Jarque-Bera test P-value = 0.80) (Table S8 in the Online Supplementary Document).
DISCUSSION
This longitudinal study provides a comprehensive assessment of MCH indicators in China from 1991 to 2023, revealing significant nationwide declines in MMR, U5MR, IMR, and NMR that outpaced the United Nations SDG 3.1 and 3.2 ahead of the 2030 timeline. These achievements not only reflect substantial improvements in health care access and quality but also underscore the effectiveness of sustained policy commitment and targeted public health interventions [21,22].
The trajectory of MCH indicator improvements was neither linear nor uniform over time, underscoring the limitations of conventional linear trend analysis in capturing the complexity of public health transitions. The application of Joinpoint regression elucidated the nonlinear trajectories of these indicators, revealing critical inflection points closely aligned with major national health interventions. The MMR decline exhibited three distinct phases, with accelerated reduction from 2005 to 2013 driven by the NRCMS (2003) improving rural health care access and the 2009 maternal safety initiative mandating hospital deliveries [23,24]. The reduced decline rate signals diminishing returns from supply-side interventions like promoting hospital delivery and expanding obstetric emergency care. This suggests a need to shift maternal health strategies from solely focusing of postpartum survival to a broader emphasis on women’s health throughout their lives. The three-phase decline in U5MR reflected a strategic evolution from emergency child survival programmes to comprehensive health system strengthening. The IMR showed six stages, with a peak decline period observed during 2002–2006, highlighting the impact of interventions such as immunisation, nutrition, and neonatal resuscitation training [25–27]. The NMR, among the most challenging indicators due to its dependence on immediate clinical capabilities, displayed five phases. The unprecedented decline in NMR and U5MR observed between 2002–2005 coincided with the nationwide rollout of the RME project, which drove the expansion of obstetric emergency networks and skilled birth attendance [28]. However, the slower decline in NMR during 1998–2002 likely reflected health system fragmentation predating the 2003, underscoring the importance of integrated service delivery in addressing neonatal emergencies. This aligns with global evidence that health-focused interventions yield rapid gains among vulnerable populations [29].
The strong correlations among MCH indicators likely reflected shared socioeconomic and health system drivers, such as female education, hospital deliveries, and insurance coverage, showing that integrated investments yield synergistic health gains [30,31]. Additionally, ADF and Johansen tests confirmed a stable, long-term equilibrium, indicating China’s MCH system functions as a dynamically coupled system. The VECM analysis established the NMR as a pivotal sentinel indicator for MCH system performance in China, with Granger- causal precedence over MMR, U5MR, and IMR, demonstrating its sensitivity to systemic changes and its central role in driving reductions across other mortality metrics.
Phased national policies, particularly NRCMS and the RME project, accelerated progress by expanding financial protection and institutional delivery coverage. This study confirmed that hospital delivery was a critical protective factor against maternal mortality, underscoring its essential role in preventing direct obstetric complications, such as those from obstetric haemorrhage and eclampsia [32]. This effect was operationalised through policies like the Rural Hospital Delivery Subsidy Project, which increased access to professional care for emergencies [33]. Furthermore, China improved the management of high-risk pregnancies and reduced mortality from pregnancy complications through the ‘special management system for critically ill pregnant women’ and ‘evaluation system for maternal mortality and critical illness’. Similarly, increased newborn visit rates, the NRCMS and the RME project, which strengthened neonatal and obstetric care networks, were associated with greater reductions in infant and neonatal mortality, providing evidence for prioritising comprehensive, programmatic interventions in resource allocation [34].
Some paradoxical short-term associations emerged during the implementation of major policies, offering important lessons for health system strengthening. For instance, the initial increase in maternal mortality following the expansion of NRCMS coverage may reflect ecological confounding, as policies were first prioritised in regions with historically high MMR and underdeveloped health infrastructure. Additionally, this may be attributed to temporary strains on service quality resulting from rapid influx of patient, alongside improvements in mortality reporting. Similarly, increased maternal system management coverage correlated with a short-term rise in U5MR, potentially reflecting delayed unintended consequences of maternal interventions on child survival outcomes. Most strikingly, contrary to expectations, higher hospital delivery rates were initially associated with an increase in neonatal mortality, likely reflecting a ‘risk concentration effect’, whereby the centralised management of high-risk pregnancies and critically ill neonates in hospital settings elevates in-hospital mortality rates among the highest-risk cases. This finding serves as a critical reminder that achieving universal hospital delivery is only the first step, its life-saving potential is fully realised only when paired with high-quality perinatal care. These patterns resonate with experiences in other LMICs. Evidence from Malawi indicates that expanding antenatal care without improving service quality fails to reduce mortality [35]. In Kenya, the introduction of free maternity care leads to a surge in facility deliveries that overwhelm emergency newborn services, resulting in an initial spike in neonatal mortality [36]. In Indonesia, the Jaminan Kesehatan Nasional has also faced comparable hurdles [37]. These findings highlight the importance of phased, equity-oriented implementation strategies that align coverage expansion with investments in clinical capacity, quality assurance, and adaptive monitoring system, particularly during initial stages of health reforms, to sustain gains and inform scalable MCH reforms in resourced-limited settings.
The differential adjustment mechanisms identified across indicators offer important implications for intervention design. Maternal and child mortality indicators demonstrated rapid error-correction capabilities, reflecting cumulative improvements in health care access and sustained national investments. Of particular note, infant mortality displayed a dual-pathway adjustment structure, suggesting the persistence of countervailing forces, potentially linked to regional disparities or delayed policy diffusion. This dynamic reflects the varying effectiveness of interventions in which both neonatal visit and the RME programme reduce IMR, but the latter shows great potential and should be prioritised for promotion. Despite short-term fluctuations influenced by confounding factors, the long-term equilibrium relationships among key MCH indicators confirm the intrinsic stability of sustained mortality reduction trajectories over time.
Impulse response analyses revealed distinct dynamic patterns among mortality indicators. The sustained positive effect of an NMR shock on both IMR and U5MR underscores the critical role of neonatal period as a sentinel event for subsequent child survival. Neonatal deaths, often stemming from intrapartum complications (e.g. birth asphyxia), congenital anomalies, or severe prematurity, demarcate a high-risk cohort whose survivors may experience lasting developmental and immunological impairments [38,39]. This underscores that reducing NMR is not merely an isolated goal but also a powerful lever for generating protective effects across infancy and early childhood. The biphasic response of MMR to an NMR shock, characterised by an initial transient reduction followed by a long-term detrimental phase, reflects the complex interplay between acute medical responses and prolonged psychosocial consequences, including maternal grief and mental health burdens that can adversely affect future reproductive outcomes and exacerbate pre-existing chronic conditions [40,41].
China’s significant advancements in MCH stem from a coordinated, system-wide strategy integrated financial access, service availability, and quality assurance within a national health framework. This holistic approach, exemplified by the synergistic rollout of the RME project, the NRCMS, and standardised community-based maternal and newborn care protocols, contrasts with the fragmented programmes seen in other countries. Initiatives like India’s Janani Suraksha Yojana and Mexico’s Seguro Popular have often achieved limited or unsustainable mortality reductions through coverage expansion alone, underscoring the fragility of reforms lacking robust primary care and continuous fiscal support [42]. China’s experience shows that strategic alignment and phased implementation enable health systems to adapt, build capacity, and correct imbalances.
Nevertheless, China’s model should be interpreted within its specific context. High-income countries like Japan and South Korea have achieved low NMR through technology-intensive, tertiary-care-accessible models that are less transferable to resource-constrained settings [43]. In contrast, many LMICs – such as Vietnam, Laos, and Papua New Guinea – face challenges reminiscent of China’s pre-2000 landscape, including fragmented rural health care, inequitable coverage, and weak referral systems, often compounded by insufficient political commitment, dispersed financing, and absent real-time accountability mechanisms [44,45]. For these settings, China’s approach offers adaptable insights rather than a blueprint for direct replication. Monitoring NMR offers a critical early-warning mechanism for MCH systems, while phased, equity-oriented policies that combine financial protection (as with NRCMS) and primary-level quality improvements (as with RME) can accelerate gains in institutional delivery and embed sustainable quality safeguards. Effective policy adaptations should be carefully tailored to local cultural norms, workforce realities, and pre-existing health financing structures.
This study makes three significant contributions to global health policy research. First, it establishes the central role of neonatal mortality in driving broader maternal and child mortality reductions by integrating VECM analysis with Granger causality tests – offering a new perspective for LMICs with fragmented health systems. Second, it treats policies as graded variables and standardises mortality metrics, addressing the limitations of binary policy dummies and dimensional heterogeneity in previous studies. The VECM framework further distinguishes short-term fluctuation from long-term equilibrium, providing superior policy evaluation for interventions with delayed effects. Finally, it offers actionable pathways for LMICs to accelerate progress towards SDG 3.2.
Limitations
The limitation of this discovery is that the national-level analysis may obscure critical urban-rural heterogeneities in policy implementation and health system capacity. While this study quantifies health service coverage effects, socioeconomic determinants such as household income disparities, maternal education gradients, and regional health care financing differentials are not incorporated as covariates. Future studies should disentangle urban-rural differentials in policy response pathways and validate precision-resource allocation models that integrate cointegration vector weights with socioeconomic confounders to optimise targeted public health interventions. Although the surveillance system’s quality control procedures are rigorous, some degree of underreporting, especially during the early 1990s, remains possible. However, the long-term decline trends are consistent and substantial, indicating that any such limitations do not materially affect our main conclusions.
CONCLUSIONS
This study establishes NMR as a sentinel indicator for MCH system performance in China, with Granger-causal precedence over other mortality metrics. Leveraging a VECM framework confirms that phased health policies, notably the NRCMS and RME initiatives, accelerate mortality declines through divergent mechanistic pathways, though transitional short-term trade-offs may emerge during policy scaling. It emphasises that institutionalising real-time NMR surveillance enables sentinel feedback for dynamic health system calibration and prioritises scaling evidence-based neonatal visit programmes as high-yield interventions. Concurrent integration of maternal-child health initiatives remains essential to mitigate transitional service disruptions during system reforms.