

Chronic kidney disease (CKD) is one of the leading causes of death and suffering in the 21st century, affecting over 10% of the global population – more than 800 million people [1–3]. End-stage renal disease (ESRD) is the final stage of CKD [4]. Haemodialysis is the predominant renal replacement therapy for ESRD patients [5]. In 2010, approximately 2.62 million patients received renal replacement therapy worldwide, and the number is expected to double by 2030 [6].
Physical inactivity is a major problem for patients with ESRD. Haemodialysis is a time-consuming and expensive treatment that imposes additional dietary and fluid restrictions. Inflammation-induced abnormal protein metabolism can exacerbate malnutrition, leading to decreased muscle mass, reduced exercise tolerance, and impaired quality of life [7–12]. This may be exacerbated by cardiovascular and pulmonary comorbidities, anaemia, hypervolemia, and fatigue following dialysis treatment [9,13]. In 2019, the clinical practice guideline for renal rehabilitation recommended exercise therapy for patients undergoing haemodialysis with a grade of 1B, indicating a strong recommendation supported by moderate-quality evidence [14]. In response, a growing number of meta-analyses and RCTs have synthesised the effects of exercise interventions in this population.
Existing meta-analyses have reported benefits of exercise across several clinical and patient-reported outcomes, but findings vary by exercise modality and outcome domain. For dialysis adequacy (Kt/V), some meta-analyses have reported significant improvements with intradialytic aerobic exercise, while others have found no effect [15,16]. For cardiorespiratory fitness (VO2 peak) and functional capacity, aerobic, resistance, and combined training have each shown positive effects, though the magnitude of benefit differs across reviews [17]. Health-related quality of life has improved inconsistently, with some meta-analyses reporting benefits only in the physical domain, while others show no significant change [18,19]. Regarding inflammatory markers, particularly C-reactive protein (CRP), several meta-analyses have demonstrated significant reductions following aerobic or combined exercise, but null findings have also been reported [20].
Although numerous meta-analyses have been conducted, several critical gaps remain. First, findings across meta-analyses are often inconsistent, even for the same outcome and exercise modality, due to differences in inclusion criteria, search dates, and analytical methods. Second, the methodological quality of meta-analyses has never been systematically appraised using a validated tool such as Measurement Tool to Assess Systematic Reviews 2 (AMSTAR 2), leaving readers uncertain which reviews are trustworthy. Third, the degree of primary study overlap among meta-analyses has not been quantified, which can lead to overestimation of precision if multiple reviews include the same original trials. Fourth, no previous overview has graded the certainty of evidence for each exercise-outcome pair using the GRADE framework, which is essential for clinical recommendations. Fifth, it remains unclear whether aerobic, resistance, or combined exercise modalities offer distinct, overlapping, or synergistic benefits for specific outcomes, as prior meta-analyses have often focused on a single modality or pooled them without stratification.
Given the fragmentation and inconsistencies in the existing evidence, a comprehensive synthesis that critically appraises methodological quality, quantifies overlap, and grades certainty by exercise modality is urgently needed. Therefore, we aimed to critically appraise the methodological quality of existing meta-analyses using AMSTAR 2, quantify primary study overlap using the Graphical Representation of Overlap for OVErviews (GROOVE) tool, grade the certainty of evidence for each exercise-outcome pair using GRADE, and provide a clinically actionable, modality-specific synthesis to guide exercise prescription in patients undergoing haemodialysis for CKD.
METHODS
We systematically evaluated and synthesised evidence from multiple meta-analyses investigating the effects of exercise interventions on outcomes in patients with CKD undergoing haemodialysis [21,22]. The methodology adhered to the guidelines outlined in the Cochrane Handbook for Umbrella Reviews of Systematic Reviews [22–24]. In the reporting, we followed the PRISMA statement and the AMSTAR 2 guidelines (Table 1) [36,37]. Two authors were responsible for the processes of literature search, study selection, data extraction, and quality assessment. Any disagreements encountered during these processes were resolved through discussion or, if necessary, by consultation with the third reviewer to reach a consensus [38].
Table 1
Methodological quality appraisal of the included systematic reviews and meta-analyses using AMSTAR 2*
| Study | Rating categories | Overall rating | |||||||||||||||
|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|---|
| 1 | 2 | 3 | 4 | 5 | 6 | 7 | 8 | 9 | 10 | 11 | 12 | 13 | 14 | 15 | 16 | ||
| Sheng et al., 2014 [25] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | Y | Y | Moderate |
| Chung et al., 2017 [26] | Y | N | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | Low |
| Young et al., 2018 [27] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | High |
| Bogataj et al., 2020 [28] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Low |
| Ferreira et al., 2019 [29] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | N | Y | Y | Low |
| Huang et al., 2019 [30] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | High |
| Kirkman et al., 2019 [31] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | N | Y | Y | Low |
| Molsted et al., 2019 [32] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | Y | Y | Moderate |
| Salhab et al., 2019 [33] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | N | Y | Y | Moderate |
| Ferrari et al., 2020 [34] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | N | Y | Y | Moderate |
| Yu et al., 2024 [35] | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | Y | High |
N – no, Y – yes
*Items 1–16 represent the methodological domains assessed using AMSTAR 2. Q1: Did the research questions and inclusion criteria for the review include the components of PICO?, Q2: Did the report of the review contain an explicit statement that the review methods were established prior to the conduct of the review, and did the report justify any significant deviations from the protocol?, Q3: Did the review authors explain their selection of the study designs for inclusion in the review?, Q4: Did the review authors use a comprehensive literature search strategy?, Q5: Did the review authors perform study selection in duplicate?, Q6: Did the review authors perform data extraction in duplicate?, Q7: Did the review authors provide a list of excluded studies and justify the exclusions?, Q8: Did the review authors describe the included studies in adequate detail?, Q9: Did the review authors use a satisfactory technique for assessing the risk of bias (RoB) in individual studies that were included in the review?, Q10: Did the review authors report on the sources of funding for the studies included in the review?, Q11: If meta-analysis was performed, did the review authors use appropriate methods for statistical combination of results?, Q12: If meta-analysis was performed, did the review authors assess the potential impact of RoB in individual studies on the results of the meta-analysis or other evidence synthesis?, Q13: Did the review authors account for RoB in primary studies when interpreting/discussing the results of the review?, Q14: Did the review authors provide a satisfactory explanation for, and discussion of, any heterogeneity observed in the results of the review?, Q15: If they performed quantitative synthesis, did the review authors carry out an adequate investigation of publication bias (small study bias) and discuss its likely impact on the results of the review?, Q16: Did the review authors report any potential sources of conflict of interest, including any funding they received for conducting the review? The overall rating represents the level of confidence in the results of each review and was classified as high, moderate, low, or critically low
Search methodology
We systematically searched Embase, PubMed/MEDLINE, the Cochrane Library, and Web of Science through January 2026. We designed the search strategy using a combination of subject terms and free words related to the core concepts. Key search terms included ‘exercise therapy’, ‘haemodialysis’, ‘renal insufficiency’, ‘chronic kidney disease’, ‘end-stage renal disease’, ‘meta-analysis’, and ‘systematic review’ (Text S1 in the Online Supplementary Document).
Study selection process
In the study selection process, we followed the Population, Intervention, Comparison, Outcomes, and Study type framework. The population inclusion criteria were: adult patients (aged ≥18 years) diagnosed with chronic kidney disease, primarily at the ESRD stage, who were undergoing maintenance haemodialysis. Intervention inclusion criteria were: intradialytic or non-intradialytic exercise interventions, including aerobic training, resistance training, or a combination of both. Comparison inclusion criteria were: control groups receiving usual haemodialysis care, no exercise, sham exercise, or low-intensity activities. Outcomes inclusion criteria were: reporting on at least one of the following outcomes – Kt/V, VO2 peak, functional capacity (six-minute walk test (6MWT)), health-related quality of life (physical component score (PCS), and mental component score (MCS) of the short-form 36 health questionnaire), systolic blood pressure (SBP) and diastolic blood pressure (DBP), CRP, depression scores, or serum phosphorus levels. Study type inclusion criteria referred to systematic reviews or meta-analyses of RCTs.
We excluded narrative reviews, letters, editorials, conference abstracts, study protocols, and network meta-analyses. Further, we excluded meta-analyses for which extractable data on intradialytic exercise outcomes could not be obtained, and studies for which the full text was unavailable. We also excluded studies that were not in English. Reviews focusing on interventions that were not relevant to the defined exercise modalities were excluded. If multiple meta-analyses from the same author group used overlapping data sets, the most recent or most comprehensive publication was selected to avoid duplication (Table S1 in the Online Supplementary Document).
Overlapping discovery and processing
If two or more meta-analyses evaluated the same outcome, the original studies they included could overlap. To quantify the extent of overlap for each outcome, we calculated the corrected covered area (CCA) using the GROOVE methodology [39]. For each outcome, we constructed a study-by-review matrix to identify all unique primary studies (r) and the total number of inclusions across the relevant meta-analyses (N). The CCA was derived as:

where ‘c’ represents the number of meta-analyses contributing to that outcome. We classified the overlap as slight (<5%), moderate (5% to <10%), high (10% to <15%), or very high (≥15%). Two reviewers independently conducted the overlap assessment using GROOVE. Any discrepancies in the interpretation of overlap were resolved by consulting a third reviewer. To manage overlapping data and minimise bias in the synthesis, we applied the following hierarchical decision rules. If there was overlap between Cochrane and non-Cochrane reviews, we prioritised results from the Cochrane review. For a high or very high degree of overlap among non-Cochrane reviews, precedence was given to the meta-analysis with the highest AMSTAR 2 quality score. If AMSTAR 2 scores were identical, the meta-analysis with the largest number of included RCTs or the most recent publication date was selected. For slight or moderate overlap, we considered and included results from all relevant meta-analyses in the descriptive summary (Figure S1 in the Online Supplementary Document).
Data extraction and quality assessment
We assessed inter-rater agreement for study selection and data extraction using Cohen’s κ. The κ value was 0.87 (95% confidence interval (CI) = 0.82, 0.92), indicating almost perfect agreement. We used a standardised data extraction form to collect the following information from each included meta-analysis: first author, publication year, journal discipline, date of the last search, number and design of included primary studies, total sample size, characteristics of the participant population, details of the exercise intervention and comparator, and all reported outcome measures with their respective effect sizes, CIs, P-values, and I2 statistic [40]. We used the GRADE approach to rate the overall certainty of evidence for each outcome, considering the entire body of evidence from all relevant meta-analyses [41]. For each outcome, two reviewers independently assessed the following domains: risk of bias, inconsistency, indirectness, imprecision, and publication bias. Each outcome was rated as having high, moderate, low, or very low certainty. Additionally, we classified the resulting evidence into four categories based on evidence classification criteria – convincing evidence (level one), highly suggestive evidence (level two), suggestive evidence (level three), weak evidence (level four), and not significant (Table 2; Table S2 in the Online Supplementary Document).
Table 2. Evidence classification criteria
| Evidence class | Criteria |
|---|---|
| I | >1000 cases (or >20,000 participants for continuous outcomes); statistical significance at P < 10−6 (random effects); no evidence of small study effects and excess significance bias; 95% prediction interval excluded null value; no large heterogeneity (I2<50) |
| II | >1000 cases (or >20,000 participants for continuous outcomes); statistical significance at P < 10−6 (random effects); the largest study with 95% CI excluding null value |
| III | >1000 cases (or >20,000 participants for continuous outcomes) and statistical significance at P < 0.001 |
| IV | Remaining significant associations with P < 0.05 |
| Non-significant | P > 0.05 |
CI – confidence interval
Data synthesis
We extracted effect estimates including mean difference (MD), weighted mean difference (WMD), standardised mean difference (SMD), 95% CIs, P-values, and I2 statistics. The I2 values were interpreted as follows: <25% low heterogeneity; 25–50% low to moderate heterogeneity; 50–75% moderate to substantial heterogeneity; and >75% substantial heterogeneity. A P-value of <0.05 for the Q-test was considered indicative of significant statistical heterogeneity. We explored significant clinical heterogeneity through subgroup analyses and, where appropriate, sensitivity analyses. Regarding the statistical model for pooling data, we used a fixed-effect model when heterogeneity was low (I2 < 25 and P ≥ 0.10), and a random-effects model (DerSimonian-Laird) when heterogeneity was moderate to substantial (I2 ≥ 25 and P < 0.10), as this accounts for variability across studies.
RESULTS
Search results
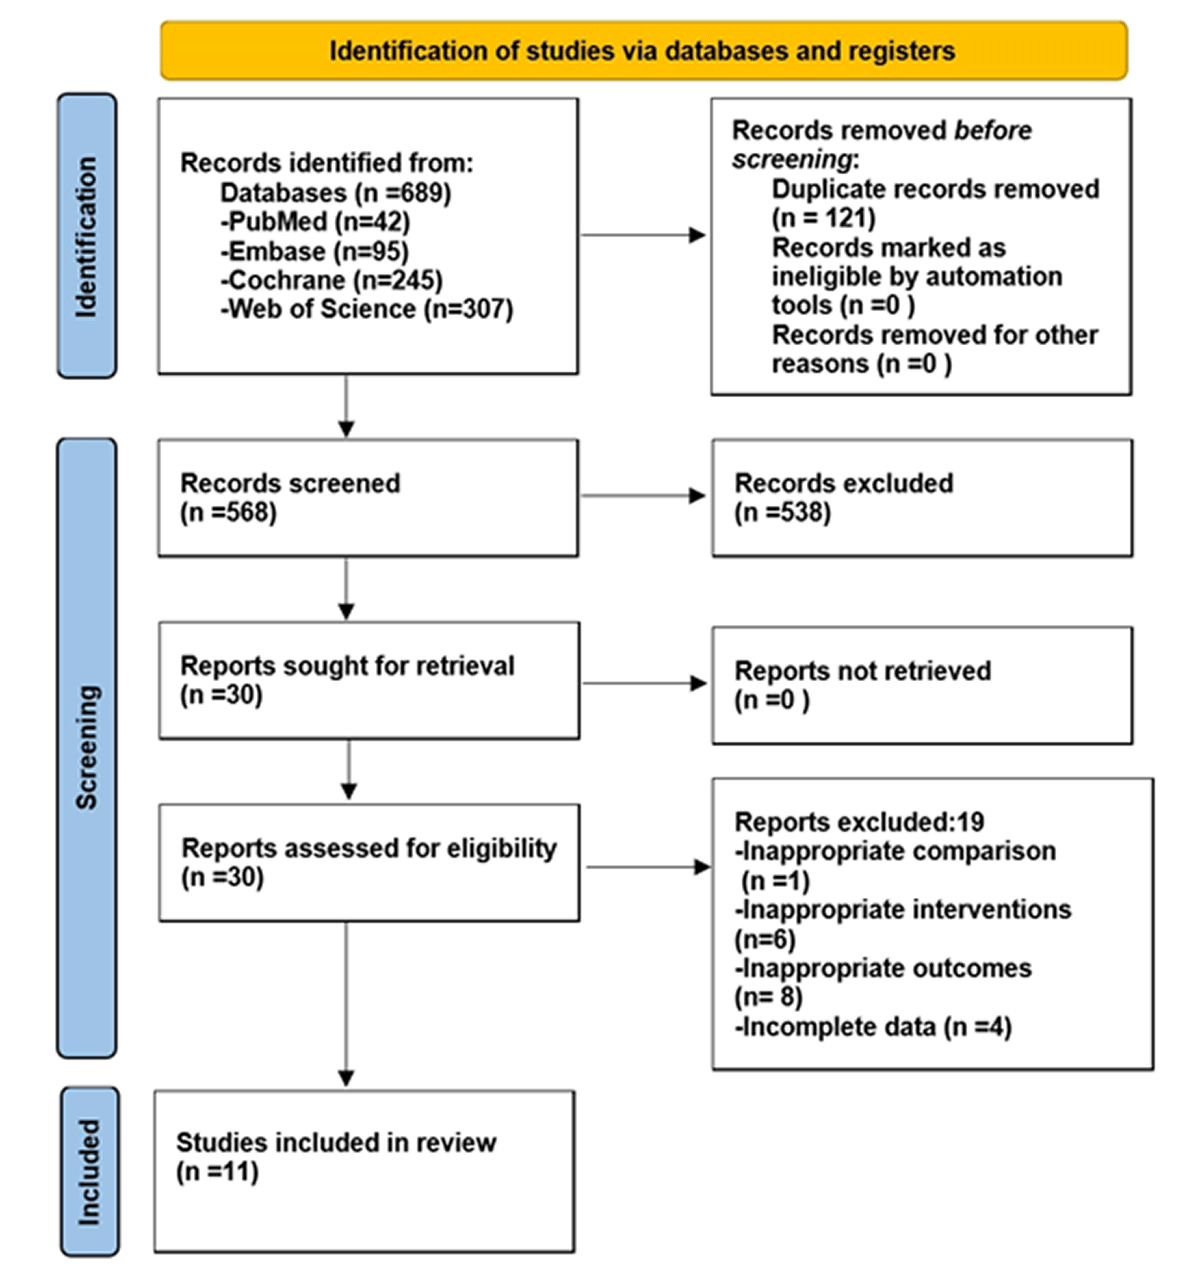
The initial search included 689 systematic reviews. After removing 121 duplicates, we screened 568 records. Of these, we excluded 538 based on the title and abstract, leaving 30 full-text reports for eligibility assessment. A further 19 were excluded through reading the full text, resulting in 11 meta-analyses included in the final analysis (Figure 1).
Figure 1. PRISMA flow diagram to show study selection.
Study characteristics
The included meta-analyses were published between 2014 and 2024 and exclusively enrolled adult patients aged >18 years. All reviews reported sample sizes [25–35], with only three exceeding 1000 participants [32,34,35]. Regarding the evidence classification of the extracted outcomes, 23 were assigned to level four, 10 to level three, and 21 were considered non-significant. According to GRADE, six outcomes were rated as moderate certainty, seven as very low, and 41 as low certainty. AMSTAR 2 appraisals revealed high methodological quality in three meta-analyses and moderate or low in the remaining four. The calculated CCA values ranged from 15.4–33.3% across outcomes, all falling into the very high overlap category. Given this substantial overlap, simply pooling all available meta-analyses would lead to severe double-counting of primary data and overestimated precision. We therefore applied pre-specified hierarchical selection rules (Cochrane priority, AMSTAR 2 rating, number of RCTs, and recency) to retain the most appropriate single meta-analysis per outcome-modality combination for the primary synthesis (Table 3).
Table 3. Basic information of the included studies
| Study | Region | Treatment | Control | Duration of exercise | Dialysis frequency | Studies included, n | Sample size | Age in years | Female, % | Last search date | Outcomes |
|---|---|---|---|---|---|---|---|---|---|---|---|
| Sheng et al., 2014 [25] | China | AT, RT | No exercise | 8–40 weeks | 3 times a week | 24 | 997 | 53.90 | 37% | February 2014 | Kt/V, VO2 peak, SF-36, and adverse events |
| Chung et al., 2017 [26] | Taiwan | AT, RT | No exercise | 8 weeks | 10–60 min, 3 times a week | 17 | 651 | NA | NA | January 2015 | 6MWT, VO2 peak, haemoglobin, albumin, depression, PCS, MCS, and adverse events |
| Young et al., 2018 [27] | UK | CT | No exercise | 14 weeks (6–26 weeks) | 31 minutes (range 20–45), twice a week | 8 | 369 | x̄ (SD) = 53.6 (11.1) | 44% | 28 February 2018 | VO2 peak, 6MWT, PCS, MCS, SBP, DBP, pulse wave velocity, and physical function |
| Bogataj et al., 2020 [28] | Slovenia | AT, RT, CT | Pre-post intervention | 12 weeks (8–40 weeks) | 13–90 min, 3 times a week | 33 | 1274 | x̄ (SD) = 55.7 (9.6) | NA | March 2019 | 6MWT, Oxygen consumption, CRP, and10-repetition sit-to-stand test |
| Ferreira et al., 2019 [29] | Brazil | RT | No exercise | 6–25 weeks | NA | 23 | NA | NA | NA | July 2018 | Creatinine, phosphate, potassium, and Kt/V |
| Huang et al., 2019 [30] | China | AT, RT, CT | Usual care or sham activity | 12 weeks (8–48 weeks) | 15–90 min, 3 times a week | 20 | 677 | x̄ (SD) = 52.0 (12.5) | 39 | November 2018 | Kt/V, SBP, DBP, VO2 peak, 6MWT, PCS, MCS, and SF-36 |
| Kirkman et al., 2019 [31] | UK | AT, RT | No exercise | 8 weeks | 60 min, 2–3 times a week | 15 | 307 | 18–76 | NA | November 2018 | Kt/V, urea, creatinine, beta-2-microglobulin, phosphate, and potassium |
| Molsted et al., 2019 [32] | NA | AT, RT, CT | Usual care or sham exercises | NA | NA | 8 | 290 | x̄ (SD) = 52.1 (13.2) | 39 | October 2017 | Muscle size, 1-5RM tests, dynamometers, 6MWT, SF36, PCS, MCS, kidney disease questionnaire, and adverse effects |
| Salhab et al., 2019 [33] | Netherlands | AT | Usual care | 8–24 weeks | 15–60 min, 2–3 times a week | 22 | 706 | 43.3–72.5 years | 40 | June 2018 | PCS, MCS, serum phosphorus, dialysis efficiency, inflammatory status, vitamin D3, parathyroid hormone, intake of phosphate binders, mortality, and hospitalisation rate |
| Ferrari et al., 2020 [34] | Brazil | AT, RT, CT | Usual care or sham exercises | 48 months | 3 times a week | 50 | 1,757 | 20–73.9 | NA | July 2019 | Kt/V, SBP, DBP, VO2 peak, 6MWT, haemoglobin, CRP, IL-6, andTC |
| Yu et al., 2024 [35] | China | AT, RT, CT | Usual care, sham exercise, and no exercise | 8–48 weeks | 20–90 minutes, 3 times a week | 22 | 1,059 | x̄ (SD) = 53.0 (10.4) | 40 | April 2023 | Beck depression inventory, self-rating depression scale, hospital anxiety, and depressive depression scale |
AT – aerobic training, CRP –C-reactive protein, CT – combined training, DBP – diastolic blood pressure, IL-6 – Interleukin-6, Kt/V – urea clearance index, MCS – mental component scores, NA – not available, PCS — physical component scores, RM – repetition maximum, RT – resistance training, SBP – systolic blood pressure, SD – standard deviation, SF-36 – short-form 36 health questionnaire, TC – total cholesterol, VO2 peak – peak oxygen consumption, 6MWT – six-minute walk test, x̄ – mean
Results of meta-analyses of functional scores
Dialysis adequacy
Regarding dialysis adequacy, Kt/V was reported in five meta-analyses [25,29,30,33,34]. After overlap management, the analysis by Ferrari et al. [34] was selected for aerobic and resistance exercise because it had the highest AMSTAR 2 score and the largest number of included studies (n = 50) among all meta-analyses reporting these modalities. For combined exercise, Huang et al. [30] was chosen as it was the only meta-analysis that specifically analysed combined training for Kt/V and had low heterogeneity (I2 = 0). Aerobic exercise significantly improved Kt/V (WMD = 0.08; 95% CI = 0.00, 0.15, P = 0.04, I2 = 56). Resistance exercise showed no significant effect (WMD = 0.10; 95% CI = −0.01, 0.20, P = 0.06, I2 = 0). Combined exercise also did not significantly affect Kt/V (SMD = 0.19; 95% CI = –0.06, 0.43, P = 0.14, I2 = 0).
Cardiorespiratory fitness
Cardiorespiratory fitness and VO2 peak were assessed in six meta-analyses [25–28,30,34]. Based on the highest AMSTAR 2 score and largest sample size, Ferrari et al. [34] was considered the best available evidence for both aerobic and combined exercise. Both aerobic (WMD = 2.07; 95% CI = 0.42, 3.72, P = 0.01, I2 = 0) and combined exercise (WMD = 5.41; 95% CI = 4.03, 6.79, P < 0.00001, I2 = 0%) significantly increased VO2 peak. No resistance-only meta-analysis reported this outcome.
Functional capacity
The 6MWT was assessed in six meta-analyses [25–28,30,34]. Following the same hierarchical approach, Ferrari et al. [34] was selected for all three modalities because it had the highest methodological quality (high AMSTAR 2), the largest number of primary studies, and the most recent search date. Aerobic training (WMD = 64.98; 95% CI = 43.96, 86.11, P < 0.00001, I2 = 0) and resistance training (WMD = 68.50; 95% CI = 29.05, 107.96, P = 0.0007, I2 = 36%) significantly improved 6MWT, whereas combined training did not (WMD = 36.37; 95% CI = –13.73, 86.46, P = 0.15, I2 = 0).
Blood pressure
Blood pressure (SBP and DBP) was reported in four meta-analyses [25,27,30,34]. Ferrari et al. [34] provided the best evidence for both aerobic and combined exercise due to its high AMSTAR 2 rating and comprehensive data extraction. Aerobic exercise significantly reduced SBP (WMD = −10.07; 95% CI = −16.35, −3.78, P = 0.002, I2 = 44) but not DBP (WMD = −2.96; 95% CI = −7.71, 1.78, P = 0.22, I2 = 65). Conversely, combined exercise significantly lowered DBP (WMD = −5.76; 95% CI = −8.83, −2.70, P = 0.0002, I2 = 0%) but not SBP (WMD = −4.33; 95% CI = −9.75, 1.08, P = 0.12, I2 = 0). No resistance-only meta-analyses reported blood pressure outcomes.
Physical and mental component scores
In the six meta-analyses, PCS and MCS were examined [25–27,30,32,33]. For aerobic exercise, Young et al. [27] was selected because it was the only meta-analysis with low heterogeneity and a specific focus on intradialytic cycling, which best represented the aerobic intervention. Aerobic exercise did not significantly improve PCS (MD = 1.97; 95% CI = –8.27, 12.22, P = 0.71, I2 = 18%) or MCS (MD = 3.37; 95% CI = −7.94, 14.68, P = 0.56). For resistance exercise, Molsted et al. [32] was the only meta-analysis reporting PCS, showing a significant improvement (MD = 10.05; 95% CI = 2.95, 17.14, P = 0.0006, I2 = 0%). For combined exercise, Huang et al. [30] was selected as the most comprehensive meta-analysis with low to moderate heterogeneity, demonstrating significant improvements in both PCS (SMD = 0.34; 95% CI = 0.09, 0.59, P = 0.007, I2 = 27) and MCS (SMD = 0.27; 95% CI = 0.02, 0.51, P = 0.03, I2 = 0%).
Inflammation
In two meta-analyses, CRP was examined [28,34]. For aerobic and resistance exercise, Ferrari et al. [34] was prioritised because of its high AMSTAR 2 quality and very low heterogeneity (I2 = 0% for aerobic, 10% for resistance). Aerobic exercise significantly reduced CRP (WMD = −3.28; 95% CI = −4.68, −1.88, P < 0.00001, I2 = 0), whereas resistance exercise did not (WMD = −0.50; 95% CI = −1.52, 0.52, P = 0.34, I2 = 10). For combined exercise, Bogataj et al. [28] provided the only available estimate, showing a significant reduction (SMD = −0.82; 95% CI = −1.04, −0.60, P < 0.001).
Depression
Depressive symptoms were evaluated in two meta-analyses [26,35]. After overlap management, Yu et al. [35] was selected as the best evidence for all three exercise modalities because it was the most recent, included the largest number of RCTs (n = 22), and had substantially lower heterogeneity for aerobic and resistance comparisons compared with the older meta-analyses. Aerobic exercise (SMD = −0.93; 95% CI = −1.32, −0.55, P < 0.001, I2 = 0) and combined exercise (SMD = −0.85; 95% CI = −1.29, −0.41, P < 0.001, I2 = 76.07) significantly reduced depression scores, while resistance exercise showed no significant effect (SMD = −0.40; 95% CI = −0.96, 0.17, P = 1.00, I2 = 0).
Serum phosphorus
Serum phosphorus was examined in two meta-analyses [29,33]. Ferreira et al. [29] was chosen as the best evidence for aerobic exercise because it provided an MD with a full 95% CIs, whereas the other meta-analysis reported only a vague non-significant statement. Aerobic exercise did not significantly affect serum phosphorus (MD = −1.06; 95% CI = −2.72, 0.60, P = 0.21, I2 = 98). No resistance or combined training data were available (Table S3 in the Online Supplementary Document).
DISCUSSION
This umbrella review provides a comprehensive and methodologically rigorous synthesis of 11 meta-analyses investigating the effects of exercise in patients undergoing haemodialysis. The findings indicate that aerobic, resistance, and combined exercise interventions confer distinct benefits across a range of clinical, functional, and patient-reported outcomes [25–35].
Aerobic exercise significantly improved Kt/V, VO2 peak, functional capacity (6MWT), SBP, CRP, and depressive symptoms. These results corroborate previous studies showing that aerobic training enhances cardiovascular function, microcirculation, and solute clearance during dialysis [42,43]. Andrade et al. [44] demonstrated that patients’ cardiorespiratory function was significantly improved by aerobic exercise. Although aerobic exercise has been associated with reductions in inflammatory markers such as CRP in several studies [45,46], this finding is not universal; other trials report no significant effect [47–49]. This discrepancy may be attributable to differences in exercise intensity, duration, or patient characteristics. Liu et al. [50] demonstrated that aerobic exercise may reduce depression levels in patients. However, the improvements in DBP, PCS, and MCS with aerobic exercise were not significant, likely due to the short intervention duration or to exercise intensity not reaching thresholds sufficient to affect these indicators. Improvement in PCS and MCS by aerobic exercise alone would also be insufficient to modify these parameters.
Resistance exercise produced robust improvements in functional capacity (6MWT) and the physical component of quality of life, yet did not influence Kt/V, CRP, or depression. Improvements in patients’ lower-extremity strength, endurance, and ability to perform activities of daily living suggest that the core benefits of resistance exercise primarily enhance muscle function rather than modulate systemic metabolism or inflammation. The improvement in PCS is in line with earlier findings. The study by Perez-Dominguez [51] similarly showed positive results in 6MWT and PCS without significant improvement in depression. However, in contrast to the present findings, a study by Deus et al. [52] showed that resistance exercise significantly improved quality of life, antioxidant capacity, and depression in dialysis patients. This should be interpreted with caution. The quality of life and emotional state of dialysis patients are generally low and are influenced by factors such as age, gender, functional status, and work status.
Combined aerobic and resistance training demonstrated the broadest range of benefits, significantly improving VO2 peak, DBP, both physical and mental quality of life, CRP, and depression. Nevertheless, there were no significant differences in urea clearance, 6MWT, or SBP. Basir and Mirzaei [53] showed improvements in cardiorespiratory fitness. Frih et al. [54] demonstrated improvements in physical and mental health, as well as in depression levels, among dialysis patients through combined exercise. Meléndez Oliva showed that combining exercise significantly improved inflammation levels [15]. Our results show that aerobic exercise was effective only in reducing systolic blood pressure, not diastolic blood pressure; the opposite was true for combined exercise. This may be due to aerobic exercise improving the compliance of large arteries but not reversing the short-term inward remodelling of small arteries, and to the reflex activation of sympathetic nerve fibres after exercise, maintaining DBP. In contrast, combined exercise counteracts the SBP-lowering effect of aerobic exercise because resistance training can elevate blood pressure through several mechanisms.
The clinical significance of some statistically significant findings warrants careful consideration. For Kt/V, the improvement with aerobic exercise (WMD = 0.08; 95% CI = 0.00l, 0.15) represents a modest absolute change. According to the Kidney Disease Outcomes Quality Initiative guidelines, a Kt/V≥1.2 is considered the minimum target for adequate dialysis [55]. An increase of 0.08 is therefore relatively small and may not be sufficient to move a patient from the insufficient to the adequate range in most cases. While statistically significant, this effect may not translate into clinically meaningful improvements in dialysis adequacy. In contrast, the improvements in the 6MWT (64.98 m for aerobic exercise, 68.50 m for resistance exercise) substantially exceed the minimal clinically important difference of 14–15 m established for exercise capacity in this population [56], suggesting clinically meaningful functional gains.
We conducted an umbrella review in accordance with established methodological guidance for overviews of systematic reviews. To ensure transparency and reproducibility, we appraised the quality of included meta-analyses using AMSTAR 2, rated outcome-specific certainty with GRADE, and quantified primary study overlap via the GROOVE tool. Despite this rigorous framework, several outcomes showed considerable statistical heterogeneity. For instance, the I2 value for Kt/V following aerobic exercise was 56%, and for depression after combined training it reached 76%. Such heterogeneity is not unexpected in this field and likely stems from multiple sources, including differences in exercise protocols such as frequency, intensity, session duration, and timing relative to dialysis sessions; variability in patient characteristics like age, comorbidities, and baseline functional status; diverse control conditions ranging from usual care to sham exercise or low-intensity activity; inconsistent outcome measurement tools and follow-up durations; and variations in dialysis prescriptions, for example low-flux vs. high-flux membranes or blood flow rates. This degree of heterogeneity limits the precision of our pooled estimates and reinforces the need for more standardised intervention protocols.
Several limitations warrant caution when interpreting our findings. The included meta-analyses may carry inherent biases; four were rated as having low methodological quality on AMSTAR 2. Furthermore, despite our use of the GROOVE tool to select the most representative meta-analysis for each outcome, primary study overlap remained substantial, potentially leading to overly precise estimates. It is also important to note that no outcome reached high GRADE certainty; 41 of 54 outcomes (76%) were rated low certainty, and seven were rated very low. Thus, although the direction of effect was consistently favourable for many outcomes, the confidence in these effect estimates is limited. Only three of the eleven included meta-analyses had sample sizes exceeding 1000 participants, meaning that most evidence derives from relatively small meta-analyses – potentially underpowered to detect modest but clinically important effects and susceptible to small-study bias. In addition, most primary RCTs lacked long-term follow-up (beyond 12 months) and used heterogeneous outcome definitions, limiting comparability across studies. Patient characteristics – such as comorbidities, concurrent medications, and baseline physical function – were often inadequately reported or controlled for in the original research. Our restriction to English-language publications may also have introduced language bias. For most outcomes, the number of available meta-analyses was too small to formally assess publication bias. Lastly, we did not perform a de novo meta-analysis of primary studies, which could have enabled more consistent data handling across studies. Taken together, these limitations argue for a cautious interpretation and cautious generalisation of our findings.
In light of the available evidence, structured exercise programs should be incorporated into the routine management of haemodialysis patients. Clinically, exercise prescriptions should be tailored to individual patient needs: aerobic exercise to improve cardiopulmonary function and dialysis efficiency; resistance training to enhance muscle strength and physical function; and combined exercise for those seeking comprehensive rehabilitation. At the policy level, implementation should be facilitated by integrating exercise professionals and equipment into dialysis units, along with insurance coverage, to improve accessibility and long-term adherence.
Future research should focus on conducting large-scale, long-term RCTs to examine the effects of exercise on hard endpoints such as hospitalisation rates and mortality. Furthermore, reporting methods for exercise parameters require standardisation to clarify optimal intensity, frequency, and duration. The biological mechanisms underpinning exercise benefits should be elucidated, including their effects on inflammatory pathways, vascular function, and neuroendocrine regulation. Research populations should be broadened to include non-English-speaking regions and patients with diverse comorbidities, thereby strengthening the generalizability of the findings. Finally, future research may develop artificial intelligence models to provide haemodialysis patients with more accessible and personalised exercise intervention programs.
CONCLUSIONS
In patients undergoing haemodialysis, aerobic exercise may improve cardiorespiratory fitness, dialysis efficiency, inflammation, and depression; resistance exercise may enhance muscle strength and physical function; and combined aerobic-resistance training may offer the broadest biopsychosocial benefits. These findings support the consideration of individualised exercise prescriptions, but high-certainty evidence is lacking. Future research should prioritise long-term trials and develop personalised exercise regimens using digital health technologies.